Dcfs Medical Form - This form is for legal custodians/guardians of minors who authorize ordinary and routine medical and/or dental care by dcfs. Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must sign below. This page includes all dcfs forms available online. Note the mo/da/yr for every dose administered. This form will aid the department in determining the physical wellness and capabilities of adults in foster or adoptive homes who are or may be. To be completed by health care provider. The day and month is required if. If you have a question about a form in particular,. Forms are available for view in either or both of the following formats: Feel free to copy these forms as needed.
Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must sign below. This form is for legal custodians/guardians of minors who authorize ordinary and routine medical and/or dental care by dcfs. Note the mo/da/yr for every dose administered. If you have a question about a form in particular,. Feel free to copy these forms as needed. Forms are available for view in either or both of the following formats: To be completed by health care provider. This page includes all dcfs forms available online. The day and month is required if. This form will aid the department in determining the physical wellness and capabilities of adults in foster or adoptive homes who are or may be.

Dcfs Medical Consent Form 2024 Printable Consent Form 2024
Feel free to copy these forms as needed. Note the mo/da/yr for every dose administered. Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must sign below. If you have a question about a form in particular,. To be completed by health care provider.

Dcfs Medical Consent Form Printable Consent Form 2022
Feel free to copy these forms as needed. If you have a question about a form in particular,. To be completed by health care provider. This form will aid the department in determining the physical wellness and capabilities of adults in foster or adoptive homes who are or may be. Note the mo/da/yr for every dose administered.

DCFS Medical Lens IRR PDF Substance Abuse Mental Disorder
This page includes all dcfs forms available online. Note the mo/da/yr for every dose administered. To be completed by health care provider. Forms are available for view in either or both of the following formats: This form is for legal custodians/guardians of minors who authorize ordinary and routine medical and/or dental care by dcfs.

food stamp application print 20152024 Doc Template pdfFiller
The day and month is required if. If you have a question about a form in particular,. This form will aid the department in determining the physical wellness and capabilities of adults in foster or adoptive homes who are or may be. This page includes all dcfs forms available online. This form is for legal custodians/guardians of minors who authorize.

Fillable Online Dcfs Employee Physical Form. Dcfs Employee Physical
Note the mo/da/yr for every dose administered. This page includes all dcfs forms available online. To be completed by health care provider. If you have a question about a form in particular,. Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must sign below.

Fillable Dcfs Form Dubois Center printable pdf download
This form is for legal custodians/guardians of minors who authorize ordinary and routine medical and/or dental care by dcfs. Note the mo/da/yr for every dose administered. To be completed by health care provider. If you have a question about a form in particular,. Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must.
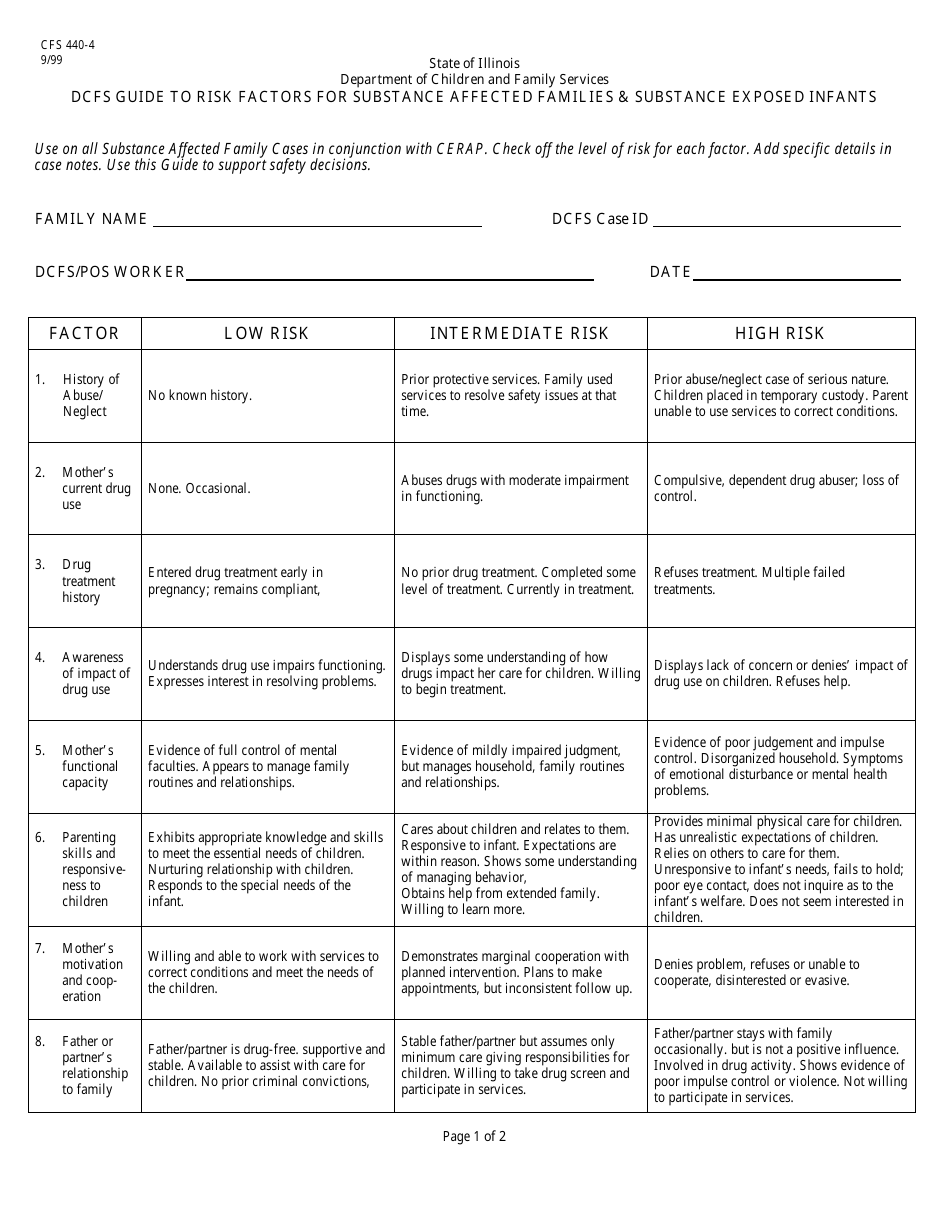
Form CFS4404 Fill Out, Sign Online and Download Fillable PDF
This form is for legal custodians/guardians of minors who authorize ordinary and routine medical and/or dental care by dcfs. This page includes all dcfs forms available online. Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must sign below. To be completed by health care provider. This form will aid the department in.

Dcfs Cw Form Cpi 2 ≡ Fill Out Printable PDF Forms Online
This form is for legal custodians/guardians of minors who authorize ordinary and routine medical and/or dental care by dcfs. Feel free to copy these forms as needed. To be completed by health care provider. Forms are available for view in either or both of the following formats: This page includes all dcfs forms available online.
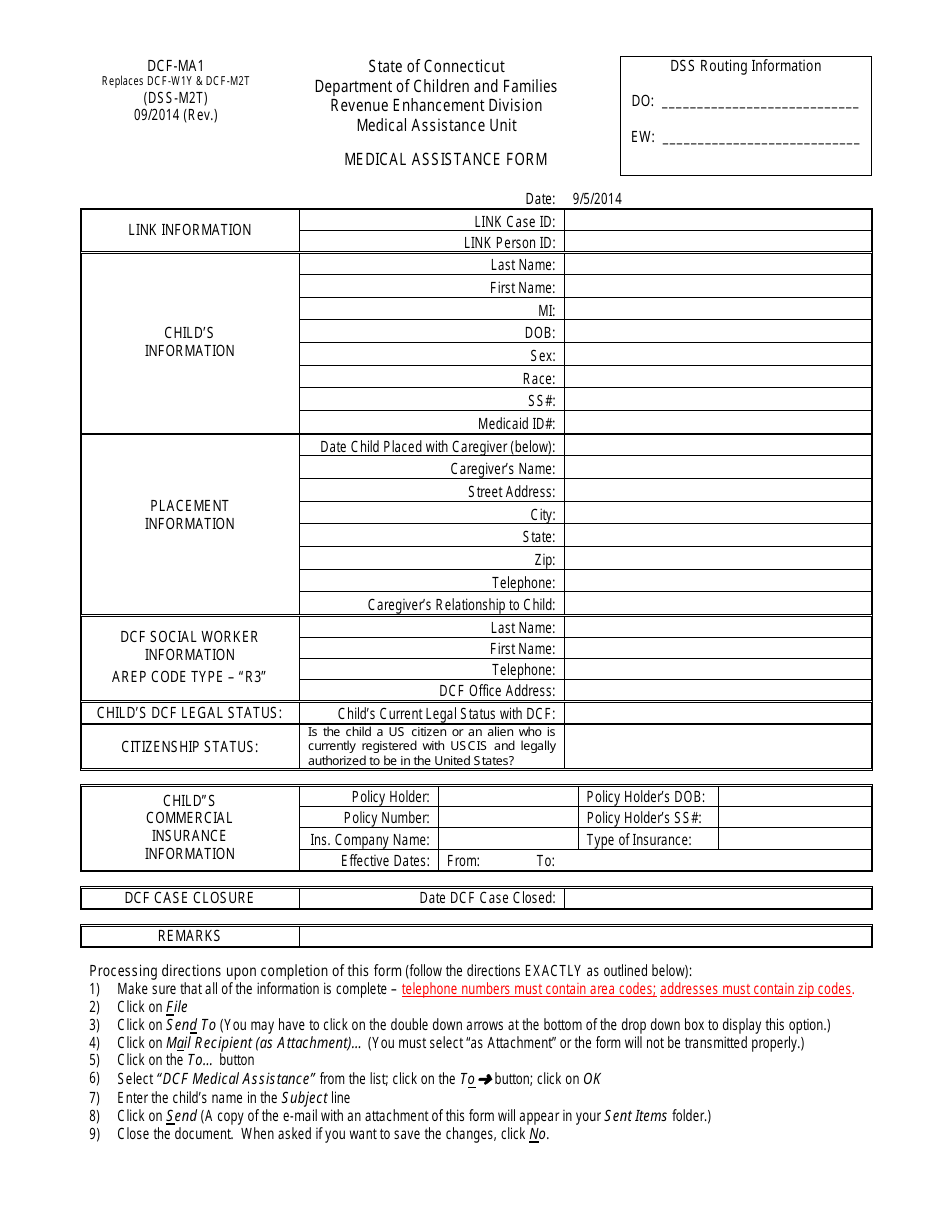
Form DCFMA1 Fill Out, Sign Online and Download Printable PDF
Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must sign below. Note the mo/da/yr for every dose administered. This form is for legal custodians/guardians of minors who authorize ordinary and routine medical and/or dental care by dcfs. The day and month is required if. If you have a question about a form.

Form Dcfs 561(B) Dental Examination Los Angeles Dcfs printable pdf
Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must sign below. If you have a question about a form in particular,. To be completed by health care provider. This form is for legal custodians/guardians of minors who authorize ordinary and routine medical and/or dental care by dcfs. Feel free to copy these.
This Form Is For Legal Custodians/Guardians Of Minors Who Authorize Ordinary And Routine Medical And/Or Dental Care By Dcfs.
Feel free to copy these forms as needed. Health care provider (md, do, apn, pa, school health professional, health official) verifying above immunization history must sign below. The day and month is required if. To be completed by health care provider.
If You Have A Question About A Form In Particular,.
This page includes all dcfs forms available online. Forms are available for view in either or both of the following formats: Note the mo/da/yr for every dose administered. This form will aid the department in determining the physical wellness and capabilities of adults in foster or adoptive homes who are or may be.